
Populations of Focus
Putting the Key Activities in Context
Person-centered population-based care
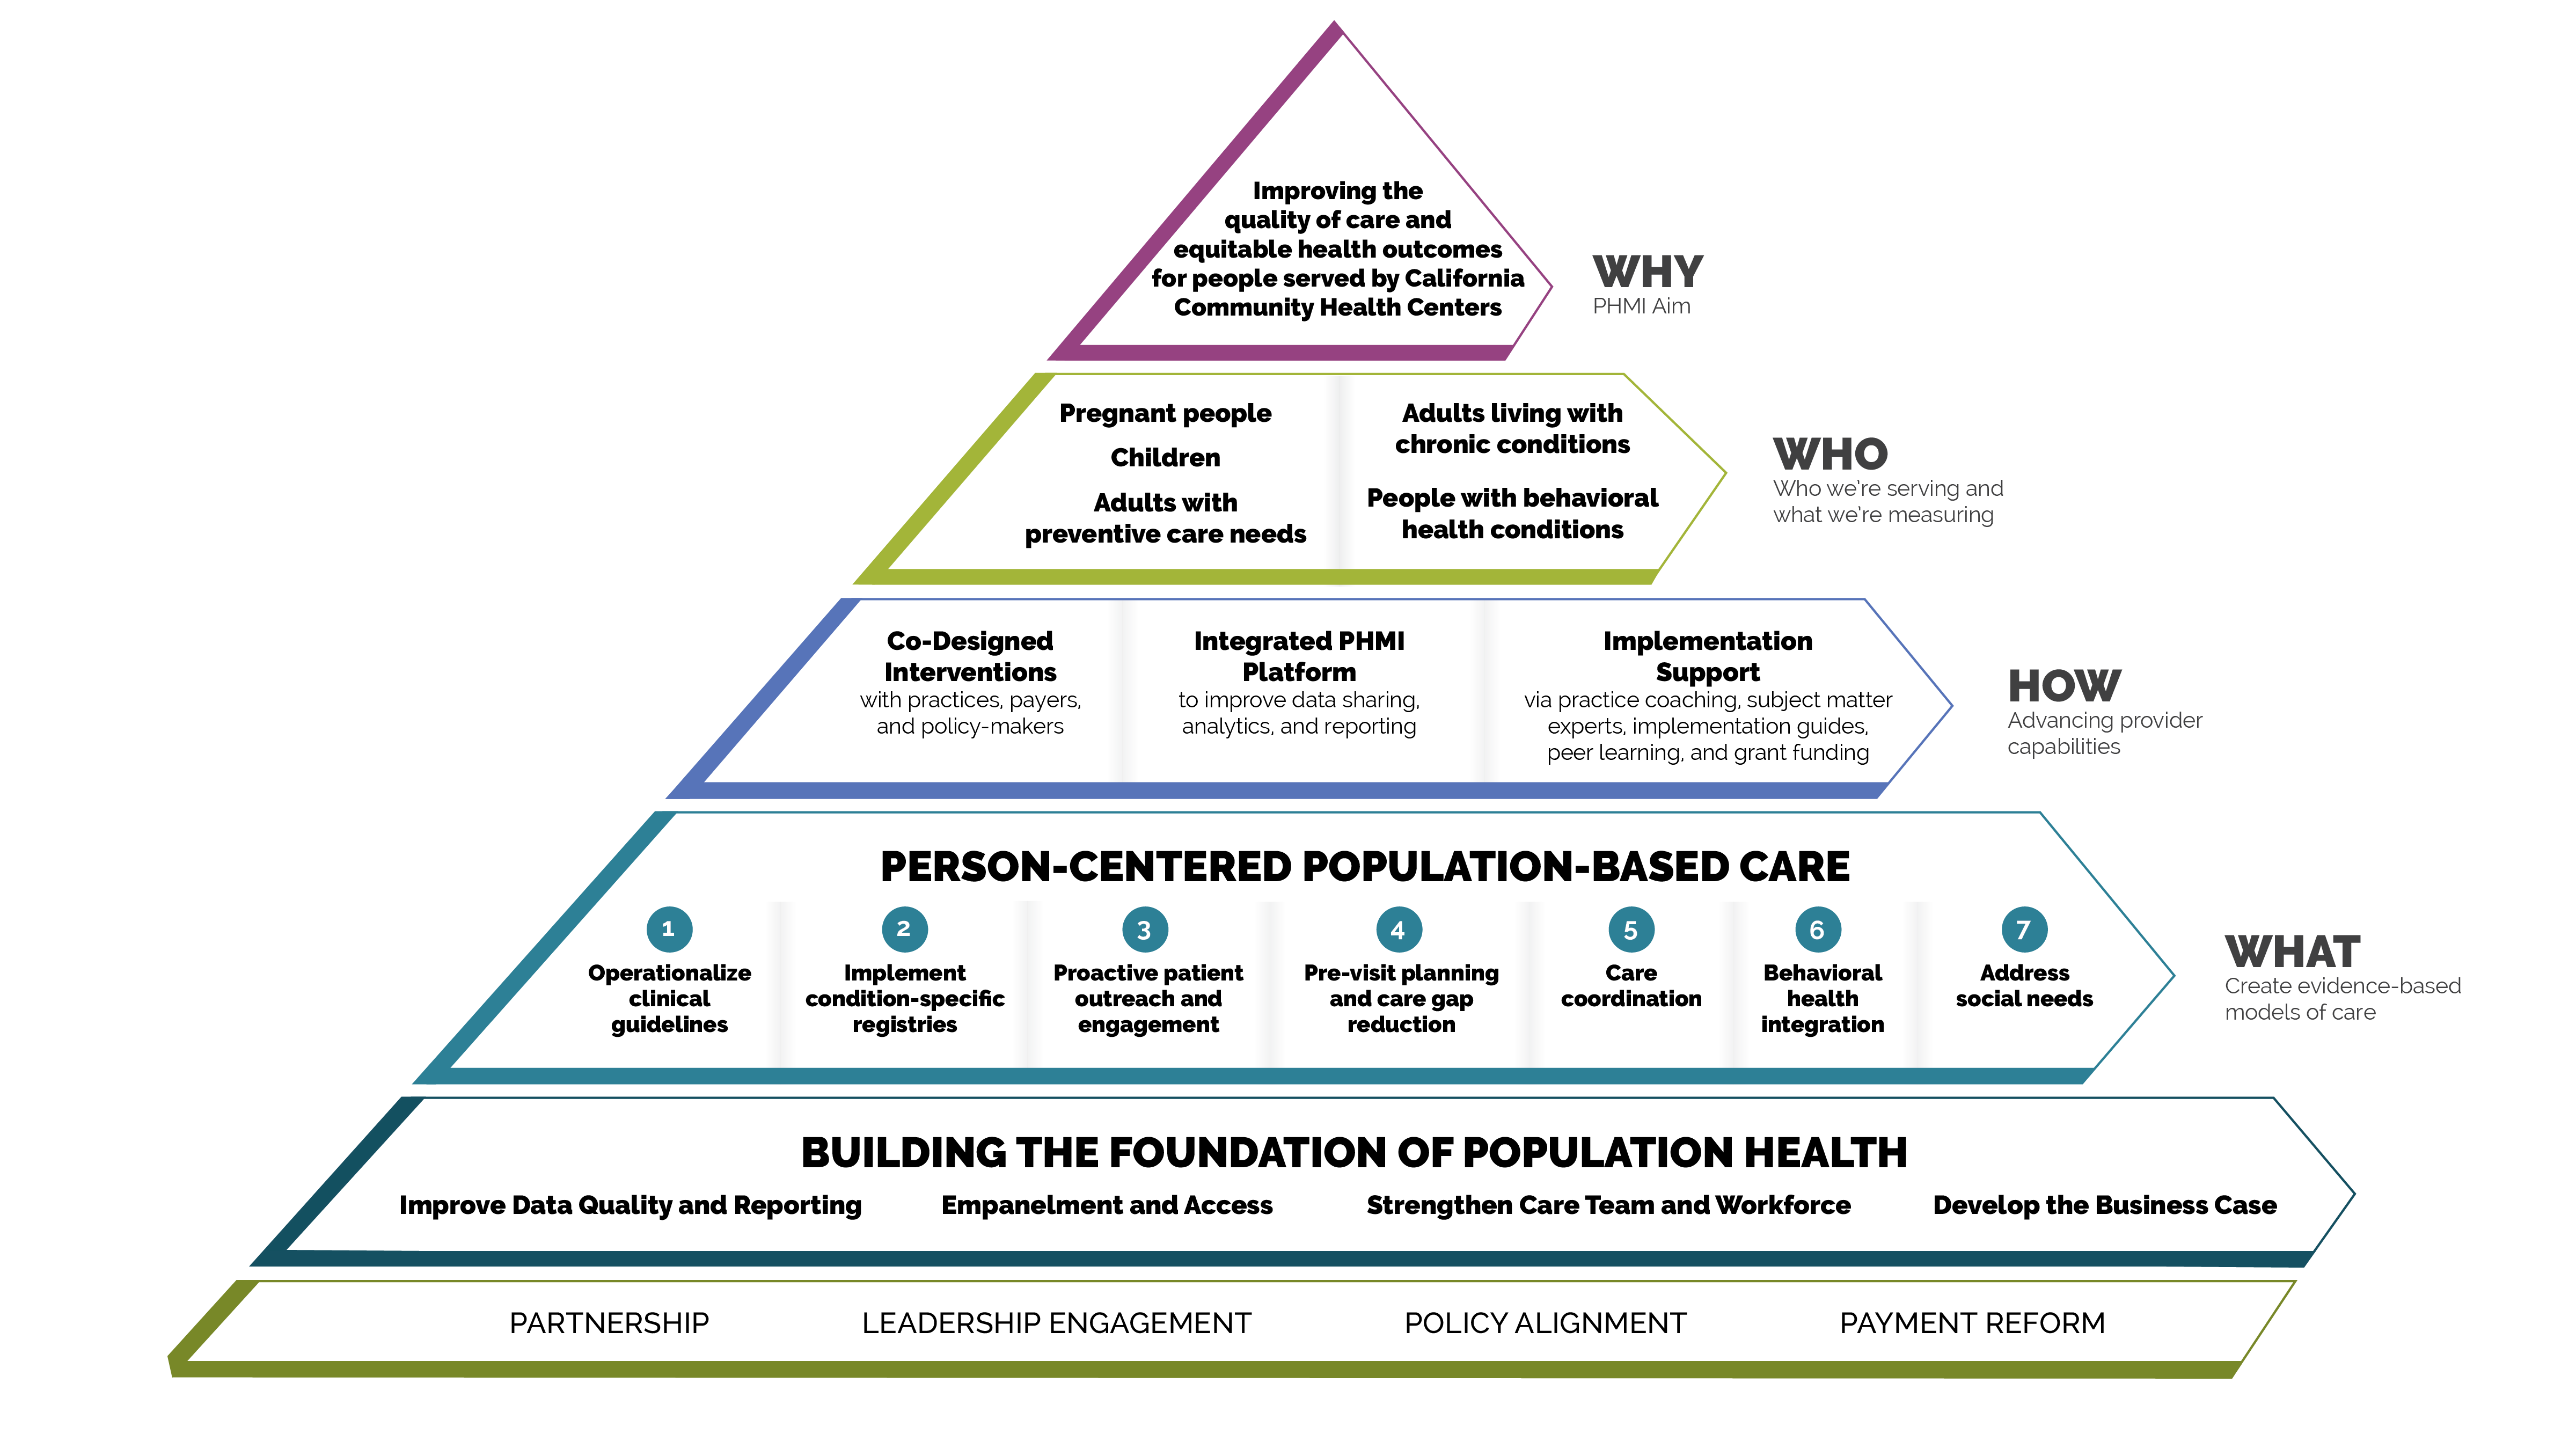
Each of the key activities advance one or more of the seven person-centered population-based care change concepts:
- Operationalize clinical guidelines.
- Implement condition-specific registries.
- Proactive patient outreach and engagement.
- Pre-visit planning and care gap reduction.
- Care coordination.
- Behavioral health integration.
- Address social needs.
FIGURE 1: PHMI IMPLEMENTATION MODEL
Core and supplemental measures
The measures covered in this guide consist of Healthcare Effective Data and Information Set (HEDIS) measures designated as core and supplemental measures by PHMI. These measures can be considered outcome measures because there is ample evidence that improved timely care will improve overall population health outcomes for prenatal and postpartum care. All measures use standard HEDIS definitions and are aligned with CalAIM and APM 2.0. For information about these measures, reference the PHMI Data Quality and Reporting Guide.
PHMI selected a few core and supplemental measures of focus for this population, though practices can track others that feel important and relevant. This guide provides detailed guidance to improve your practice’s results on the following four core and supplemental measures for pregnant people:
- Prenatal and Postpartum Care (Core Measure).
- Prenatal and Postpartum Care (Timeliness of Prenatal Care) (Supplemental Measure).
- Prenatal Depression Screening and Follow-Up (Supplemental Measure).
- Postpartum Depression Screening and Follow-Up (Supplemental Measure).
Core HEDIS Measures for PHMI
|
PHMI Populations of Focus |
Measures |
|---|---|
Pregnant people |
Prenatal and Postpartum Care Percentage of people with a postpartum visit within seven to 84 days after delivery. |
Supplemental HEDIS Measures for PHMI
|
PHMI Populations of Focus |
Measures |
|---|---|
Pregnant people |
Prenatal and Postpartum Care (Timeliness of Prenatal Care) Percentage of deliveries in which people had a prenatal care visit in the first trimester. |
Prenatal Depression Screening and Follow-Up Percentage of deliveries in which people were screened for clinical depression while pregnant and, if screened positive, received follow-up care. Two rates are reported:
|
|
Postpartum Depression Screening and Follow-Up Percentage of deliveries in which people were screened for clinical depression during the postpartum period and, if screened positive, received follow-up care. Two rates are reported:
|
Measurement strategy and learning system
The core and supplemental measures are part of a larger measurement strategy and learning system, as outlined in Appendix A: Sample, Idealized System Diagram. Key Activity 1: Convene a Multidisciplinary Implementation Team Focused on Pregnant and Postpartum People outlines how your practice can develop a robust measurement system to support this work. In addition to quality assurance and monitoring, measures are also used during practice operations alongside other data for learning to
- Guide the actions of the multidisciplinary implementation team as they use a systematic approach to decreasing inequities and supporting the implementation of key activities across the practice.
- Support the care team’s efforts to advance population health and reduce care gaps through daily, weekly and monthly workflows, as well as continuous identification of opportunities for improvement.
Clinical practice guidelines
The PHMI Clinical Guidelines Advisory Group (CGAG) was established to create a standardized approach to review, adopt and promote established clinical guidelines in the PHMI cohort. For pregnant people, guidance includes prenatal care initiation and prenatal and postpartum depression. For more information, please see the Clinical Practice Guidelines for Key Medi-Cal Populations of Focus.
FIGURE 2: CLINICAL GUIDELINES: PRENATAL AND POSTPARTUM CARE (TIMELINESS OF PRENATAL CARE)
Source |
National Committee for Quality Assurance (NCQA) Healthcare Effectiveness Data and Information Set (HEDIS) |
PHMI measure |
Prenatal and Postpartum Care (Timeliness of Prenatal Care) |
Guideline language |
Ensure a prenatal care visit occurs during the first trimester for pregnant people. |
Definitions |
First trimester: 280 to176 days prior to delivery (or estimated delivery date (EDD)). Prenatal care: Any of the following where the practitioner type is an OB/GYN or other prenatal care practitioner or primary care provider (PCP) meet criteria for a prenatal visit:
|
FIGURE 3: CLINICAL GUIDELINES: PRENATAL AND POSTPARTUM CARE (TIMELINESS OF POSTPARTUM CARE)
Source |
|
PHMI measure |
Prenatal and Postpartum Care (Timeliness of Postpartum Care) |
Guideline language |
Conduct a postpartum visit in the first three weeks after delivery with a maternal care provider for persons who have delivered a live birth in any setting. After the initial assessment, provide ongoing care as needed, concluding with a comprehensive postpartum visit no later than 12 weeks after birth. |
Definitions |
Postpartum care: Documentation of a postpartum visit to an OB/GYN practitioner, midwife, family practitioner or other PCP. Must include a note indicating the date when a postpartum visit occurred and one of the following:
|
FIGURE 4: PERINATAL DEPRESSION SCREENING AND FOLLOW UP (PRENATAL)
Guideline Source |
Kaiser Permanente Southern California (December 2022) |
PHMI Measure |
Prenatal Depression Screening and Follow Up (PND-E) |
Guideline Language |
Prenatal Depression Screening (Kaiser Permanente National Guideline Program): Prenatal depression screening is recommended in the first 12 weeks. |
FIGURE 5: PERINATAL DEPRESSION SCREENING AND FOLLOW UP (POSTPARTUM)
Guideline Source |
|
PHMI Measure |
Postpartum Depression Screening and Follow Up (PDS-E) |
Guideline Language |
Postpartum Depression Screening (ACOG): Postpartum depression screening is recommended once during the postpartum period. |
Utilizing this guide to improve equitable outcomes
Many key activities in this guide include considerations for utilizing the intervention to improve equitable health outcomes and reduce the effects of racism, bias and discrimination. Key Activity 4: Use a Systematic Approach to Decrease Inequities describes key action steps for how to make an intentional and explicit effort to identify inequities, understand root causes, and reduce those inequities.
This guide also offers resources for going deeper into organizational and ecosystem-level work to advance equitable outcomes through Key Activity 18: Strengthening Community Partnerships and Key Activity 20: Strengthening a Culture of Equity. More information about this approach can be found in the PHMI Equity Framework and Approach.
Integrating behavioral health screening
Integrated behavioral health supports are important for pregnant people, as behavioral health support is likely to boost perinatal health outcomes and enhance patients’ quality of life. One foundational change is to ensure that the care team includes behavioral health staff as core members of the team; this is covered in detail in the Care Teams and Workforce Guide.
To learn more about strategies for behavioral health integration see Getting Started with Behavioral Health Integration and the PHMI Behavioral Health Guide Key Activity 2: Enhance the Culture of Integrated Behavioral Healthcare and Key Activity 3: Enhance Operational Integration of Behavioral Health.
We also offer a resource, the Pre-Visit Planning – Gaps in Care Tool, which includes recommended behavioral health screenings.
For pregnant people, foundational key activities include Key Activity 10: Implement Behavioral Health Screening, Including Postpartum Depression. Throughout the key activities in this guide, we have incorporated considerations for providing trauma-informed care and have included a resource for Implementing Population Health Management in Trauma-Informed Ways. For additional information about managing behavioral health conditions beyond screening, please see the Behavioral Health Implementation Guide.
Utilizing this guide to attend to patients’ social needs
For many key activities in this guide, we have highlighted considerations related to social needs at the individual or population level, such as expanding referral networks. A foundational activity is Key Activity 9: Use Social Needs Screening to Inform Patient Treatment Plans, which can help practices better understand and support patient- and population-level needs. Practices can help patients make connections to resources in the community to address issues such as nutrition, childcare, legal and health education needs. For Medi-Cal patients and families with high levels of social need, such as those experiencing homelessness, referrals to Enhanced Care Management and community support programs are available. See Key Activity 19: Provide Care Management for more.
For going deeper in this area, practices can utilize Key Activity 17: Continue to Develop Referral Relationships and Pathways for common social needs and Key Activity 18: Strengthen Community Partnerships to build upon the strengths, infrastructure and resources available in the community. More information about this dual patient- and population- level approach is available in the PHMI Social Health Framework and Approach.
Our theory of change
Our theory of change is that if practices implement the activities contained in this guide, it will lead to improved health and wellbeing outcomes among the pregnant people served by practices. See Appendix B: Theory of Change for a suggested driver diagram.