
Populations of Focus
Putting the Key Activities in Context
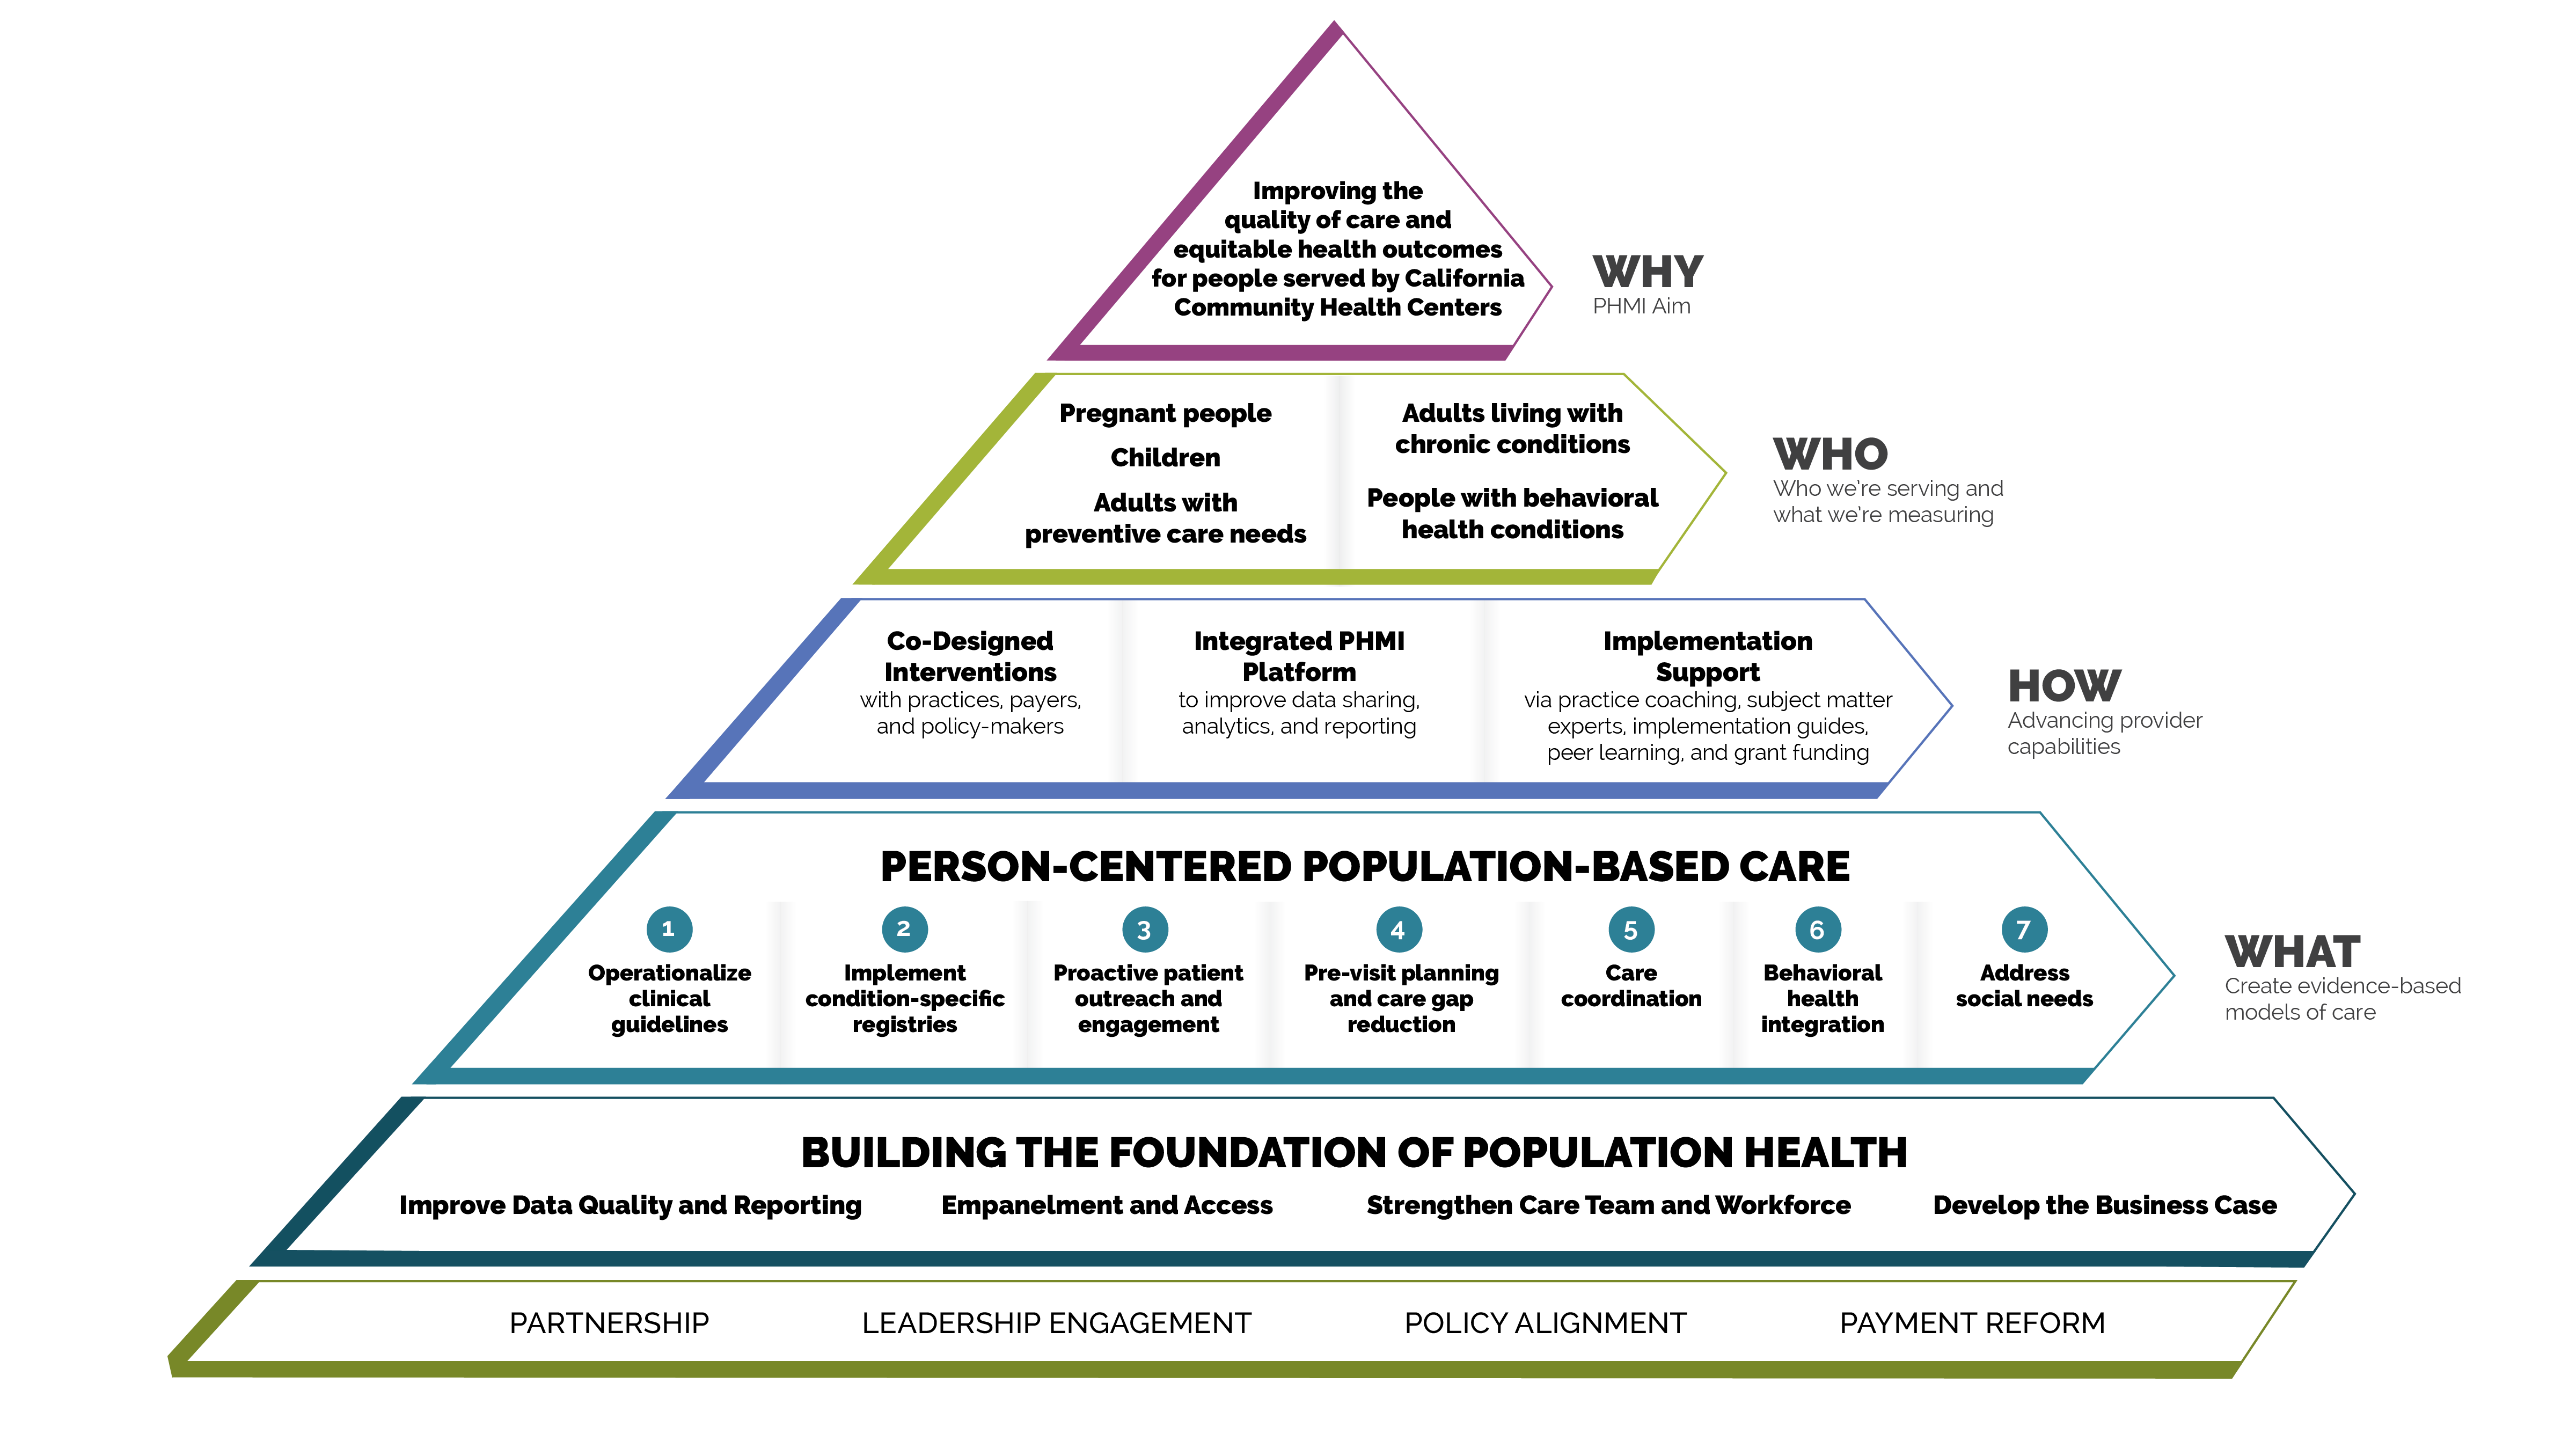
Person-centered population-based care
Each of the key activities advance one or more of the seven person-centered population-based care change concepts:
- Operationalize clinical guidelines.
- Implement condition-specific registries.
- Proactive patient outreach and engagement.
- Pre-visit planning and care gap reduction.
- Care coordination.
- Behavioral health integration.
- Address social needs.
FIGURE 1: PHMI IMPLEMENTATION MODEL
Core and supplemental measures
The measures covered in this guide consist of Healthcare Effective Data and Information Set (HEDIS) measures designated as core and supplemental measures by the Population Health Management Initiative (PHMI). All measures use standard HEDIS definitions and are aligned with California Advancing and Innovating Medi-Cal (CalAIM) and Alternative Payment Methodology (APM 2.0). For information about these measures, reference the Data Quality and Reporting Guide.
PHMI selected a few core and supplemental measures of focus for this population, though practices can track others that feel important and relevant. This guide provides detailed guidance to improve your practice’s results on the following two core measures and three supplemental measures for adolescents and families:
- Childhood Immunization Status (core measure).
- Well-child Visits in First 30 Months of Life (core measure).
- Child and Adolescent Well-Care Visits (supplemental measure).
- Immunization for Adolescents (Combo 2) (supplemental measure).
- Well-child Visits in First 30 Months of Life (15 to 30 months) (supplemental measure).
CORE HEDIS MEASURES FOR PHMI
PHMI Population of Focus |
Measure |
|---|---|
Children |
Childhood Immunization Status Percentage of two-year-old children who have received the 10 reported vaccines* *As of October 2023, there are 11 recommended vaccines. However, the RSV vaccine has not yet been incorporated into HEDIS measures. |
|
Well-Child Visits in First 30 Months of Life Percentage of children who have had six or more well-child visits in their first 15 months of life. |
SUPPLEMENTAL MEASURES FOR PHMI
PHMI Population of Focus |
Measure |
|---|---|
Children |
Child and Adolescent Well-Care Visits Percentage of children three to 21 years of age who received one or more well-care visits with a primary care practitioner or an OB/GYN practitioner during the measurement year. |
|
Immunization for Adolescents (Combo 2) Percentage of adolescents 13 years of age who had one dose of meningococcal vaccine, one Tdap vaccine and the complete human papillomavirus (HPV) series (i.e., two doses separated by 6-12 months) by their thirteenth birthday. |
|
|
Well-Child Visits in First 30 Months of Life (15 to 30 months) Percentage of children who turned 30 months old during the measurement year, and had at least two well-child visits with a primary care physician in the last 15 months. |
Measurement strategy and learning system
The core and supplemental measures are part of a larger measurement strategy and learning system, as outlined in Appendix A: Sample, Idealized System Diagram: Weaving Your Measurement Strategy and Learning System into Practice Operations. Key Activity 1: Convene a Multidisciplinary Implementation Team Focused on Pediatrics outlines how your practice can develop a robust measurement system to support this work. In addition to quality assurance and monitoring, these measures are also used during practice operations alongside other data for learning to:
- Guide the actions of the multidisciplinary implementation team as they use a systematic approach to decreasing inequities and support implementing key activities across the practice.
- Support the individual care team’s efforts to advance population health and reduce care gaps through daily, weekly and monthly workflows, as well as continuous identification of opportunities for improvement.
Clinical practice guidelines
The PHMI Clinical Guidelines Advisory Group (CGAG) was established to create a standardized approach to review, adopt and promote established clinical guidelines in the PHMI cohort. For pregnant people, guidance includes prenatal care initiation and prenatal and postpartum depression. For more information, please see the Clinical Practice Guidelines for Key Medi-Cal Populations of Focus.
FIGURE 2: CLINICAL GUIDELINES: WELL-CHILD VISITS IN FIRST 30 MONTHS OF LIFE (FIRST 15 MONTHS)
Guideline source |
|
PHMI measure |
Well-Child Visits in First 30 Months of Life (First 15 Months) |
Definitions |
Well-child visit (WCV): The WCV must occur with a primary care provider (PCP), but that PCP does not have to be the practitioner assigned to the child. Documentation includes all five of the following components:
|
Guideline language |
Conduct WCVs as a newborn; at three to five days old; by one month; and then at two, four, six, nine, 12 and 15 months. If a child comes under care for the first time at any point on the schedule, or if any items are not accomplished at the suggested age, the schedule should be brought up to date at the earliest possible time. |
FIGURE 3: CLINICAL GUIDELINES: CHILD AND ADOLESCENT WELL-CARE VISITS
Guideline source |
|
PHMI measure |
Child and Adolescent Well-Care Visits |
Definitions |
Well-child visit (WCV): The well-care visit must occur with a PCP or an OB/GYN practitioner, but the practitioner does not have to be the practitioner assigned to the individual. Documentation includes all five of the following components:
|
Guideline language |
Conduct annual well-care visits for persons three to 21 years of age. |
FIGURE 4: IMMUNIZATIONS FOR ADOLESCENTS
Guideline Source |
Centers for Disease Control and Prevention/Advisory Committee on Immunization Practices (2024) |
PHMI Measure |
Immunizations for Adolescents (IMA) |
Guideline Language |
|
Utilizing this guide to improve equitable outcomes
Many key activities in this guide include considerations for utilizing the intervention to improve equitable health outcomes and reduce the effects of racism, bias and discrimination. Key Activity 5: Use a Systematic Approach to Decrease Inequities describes key action steps for how to make an intentional and explicit effort to identify inequities, understand root causes, and reduce those inequities. Refer to existing data sources and reports that illuminate existing inequities, such as the 2021 Health Disparities Report.
This guide also offers resources for going deeper into organizational and ecosystem-level work to advance equitable outcomes such as what is outlined in Key Activity 23: Strengthen a Culture of Equity. More information about this approach can be found in the PHMI Equity Framework and Approach.
Integrating behavioral health
Integrated behavioral health supports are important for children and their caregivers, as behavioral health support is likely to boost health outcomes and enhance patients' quality of life. One foundational change is to ensure that the care team includes behavioral health staff as core members of the team. This is covered in detail in the Care Teams and Workforce Guide.
To learn more about strategies for behavioral health integration see Getting Started with Behavioral Health Integration and the PHMI Behavioral Health Guide Key Activity 2: Enhance the Culture of Integrated Behavioral Healthcare and Key Activity 3: Enhance Operational Integration of Behavioral Health.
For children, foundational key activities for integrating behavioral health include Key Activity 7: Attending to Social and Emotional Development During WCVs and Key Activity 8: Providing Dyadic Care: Screen for Postpartum Depression. Throughout these and other key activities in this guide, we have incorporated considerations for providing trauma-informed care, detailed in Key Activity 12: Implement Trauma-Informed Care Approach Across the Patient Journey. For going deeper in behavioral health integration, practices can refer to Key Activity 22: Adopt and Sustain Dyadic Care to Provide Integrated, Family-Centered Services, and Key Activity 18: Continue to Develop Referral Relationships and Pathways for specialized behavioral health services.
Of note for California Medi-Cal, there are multiple considerations and complexities in integrating behavioral health. As one example, the behavioral health benefit is divided into mild to moderate versus severe mental health conditions; the clinicians qualified and contracted to provide this care are often different. As such, early on in the behavioral health evaluation process, a clinician must decide whether a client is at the mild to moderate or severe end of the spectrum. For mild to moderate, the Medi-Cal Managed Care Plan (MCP) provides the benefit, whereas for severe, the county mental health system is responsible.
Utilizing this guide to attend to patients’ social needs
The AAP/Bright Futures recommends integrating social drivers of health into primary care to assess family access to resources necessary for optimal child development.[1] For many key activities in this guide, we have highlighted considerations related to social needs at the individual or population level, such as expanding clinic hours. A foundational activity is Key Activity 7A: Develop a Screening Process for Social Needs and Adverse Childhood Experiences (ACES) that Informs Patient Treatment Plans which can help practices better understand and support patient- and population-level needs. Practices can help patients and families and make connections to resources in the community to address issues such as childcare, parenting, legal and health education needs. For Medi-Cal patients and families with high levels of social need, such as those experiencing homelessness, referrals to Enhanced Care Management (ECM) and Medi-Cal Community Supports services are available; see Key Activity 17: Provide Care Management for Individuals with Complex Needs for more.
For going deeper in this area, practices can refer to Key Activity 18: Develop Referral Relationships and Pathways for common social needs Key Activity 20: Strengthen Community Partnerships to build upon the strengths, infrastructure and resources available in the community. More information about this dual patient- and population-level approach is available in the PHMI Social Health Framework and Approach.